What the Gap Measures
The gap value is a useful way to assess electrolyte balance and assist in identifying causes of metabolic acidosis. It is not a direct measurement of a single component in blood chemistry. Instead, it is a calculated value that reflects the difference between commonly measured positive and negative ions in the plasma.
An anion gap calculator helps medical users quickly determine whether there may be extra additional anions present. These may appear in conditions that affect pH balance, especially when the blood shows a pattern consistent with metabolic acid-base abnormality.
In simple terms, the anion gap contrasts measured sodium against measured chloride and bicarbonate. Because those three values are usually included in an chemistry panel, the calculation is straightforward to apply in routine care. The result can support clinical assessment of an electrolyte imbalance, especially when a patient has reduced bicarbonate or other signs of acid retention.
Although the anion gap is often taught as a standalone concept, it is most useful when interpreted alongside other laboratory values, symptoms, and the larger pattern of the blood chemistry. A normal result does not always rule out disease, and an abnormal result does not stand alone as a diagnosis. It is a diagnostic tool that helps narrow the possibilities.
How to Apply an Anion Gap Calculator Using Serum Sodium
A dependable anion gap calculator typically asks for three numbers: serum sodium, serum chloride, and serum bicarbonate. These are usually reported as part of a standard metabolic panel or a similar lab panel. The calculator then runs the same arithmetic a clinician would use manually.
Using the calculator is straightforward:
- Enter the serum sodium level. Provide the serum chloride value. Input the serum bicarbonate value. Examine the output and match it with the normal reference range.
As serum sodium anchors the formula, the calculator shows the balance between major measured cations and anions. A change in sodium, chloride, or bicarbonate can alter the result, which is why the calculator is useful for acid base interpretation.
As an example, a patient with a normal sodium level but a reduced bicarbonate and increased chloride may still have a normal anion gap. Another patient with reduced bicarbonate and no compensatory chloride rise may have a high anion gap. The calculator makes clear that pattern efficiently.
As you review the result, consider whether the numbers match the broader clinical picture. If the patient has vomiting, dehydration, diabetes, kidney disease, or suspected poisoning, the calculated gap becomes more informative. The same is true when comparing serial values over time, since shifting electrolytes can show whether a metabolic state is getting better or getting worse.
Formula for the Anion Gap and Detailed Computing
A common anion gap formula is written as:
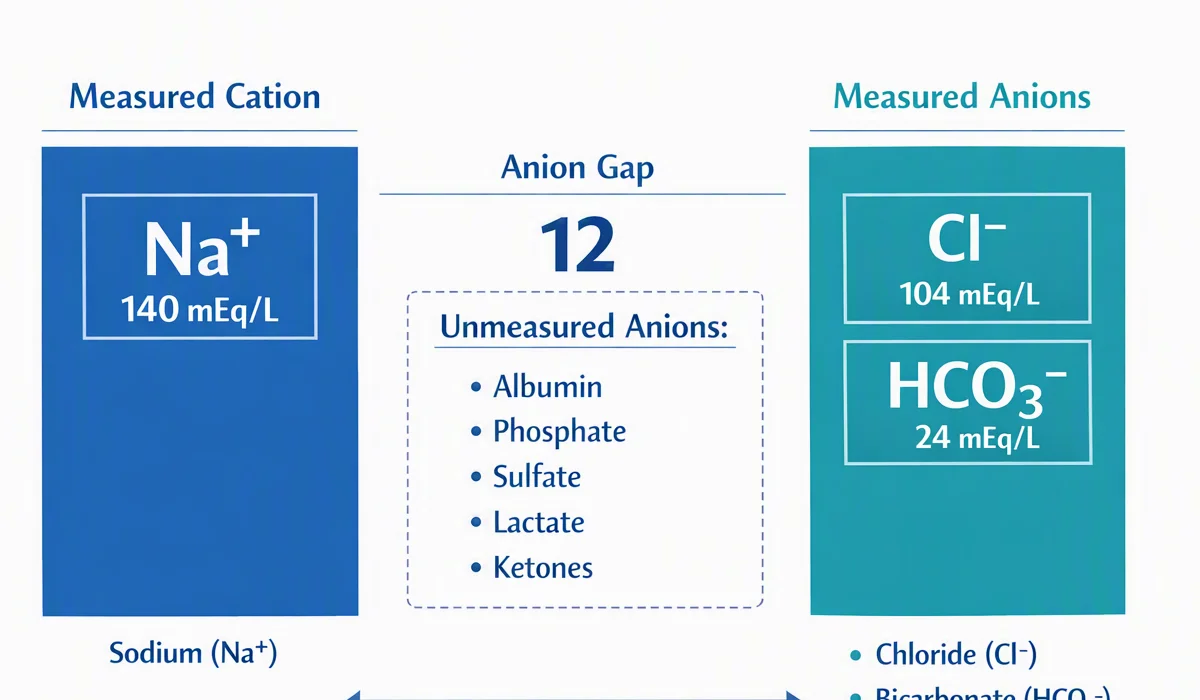
Anion gap = sodium − (chloride + bicarbonate)
Some laboratories use slight variations, but this version is the most widely used and is the simplest to understand for manual calculation. It uses the measured sodium, chloride, and bicarbonate values from the blood.
Here is a simple way to work out anion gap:
- Take the measured sodium value. Combine the measured chloride and bicarbonate values. Take away that total from sodium. The result is the anion gap.
Example:
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Working: 140 − (104 + 24) = 12
The outcome is usually in the expected range. In this example, the blood chemistry suggests a balanced relationship among the major measured ions.
Why is this useful? Because the body contains both measured ions and unmeasured anions. The formula estimates the difference between positively charged and negatively charged components in the plasma. If the number is higher than expected, it may reflect extra acids or other unmeasured substances. That is why the anion gap is valuable in evaluating metabolic acidosis and related conditions.
Some people prefer to think about the formula as a shortcut for identifying whether the acid-base system is stable. If bicarbonate drops and chloride does not rise enough to offset it, the gap changes. If bicarbonate drops and chloride rises in parallel, the gap may remain normal even though there is still a major acid-base issue.
Normal Interval and Understanding Results
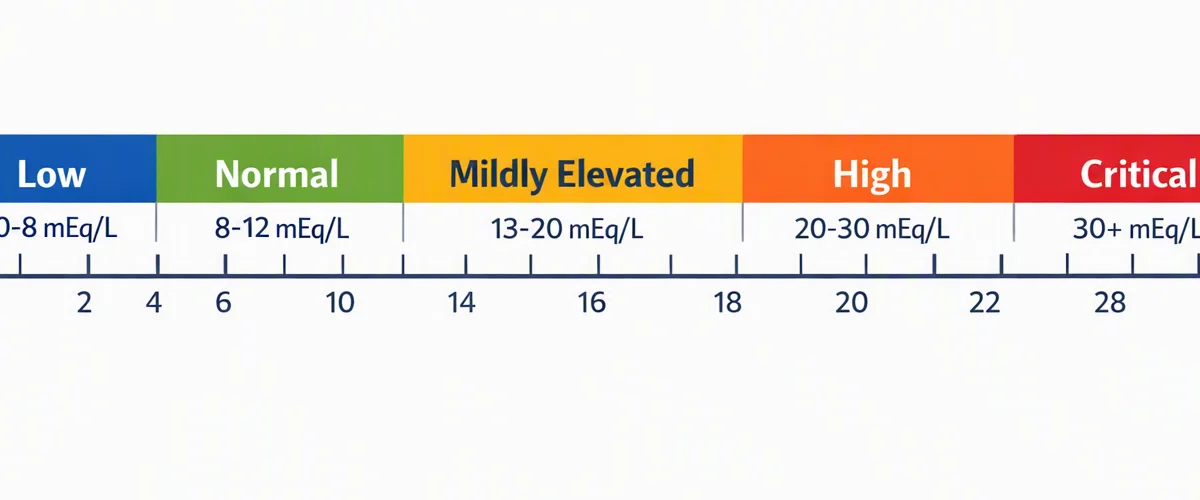
The anion gap within normal limits is often reported within a narrow reference range for normal values, but the specific interval depends on the laboratory method and the analyzer used. For that reason it is important to interpret results using the reference range provided with the test instead of relying on a single universal number.
In general, a normal anion gap suggests that measured serum electrolytes are relatively balanced and that there is no obvious accumulation of many unmeasured acids. Still, normal results do not exclude every acid-base problem. A patient can still have acidosis, especially non-gap forms where chloride increases to keep the overall balance stable.
A elevated anion gap suggests that extra acids or other unmeasured anions are present. This finding often points toward metabolic acidosis and should prompt a deeper look at causes such as lactate, ketones, kidney dysfunction, or toxins. The result is not a diagnosis by itself, but it is a valuable clue.
Albumin also matters because it is a major unmeasured negatively charged protein in plasma. When albumin is low, the measured gap may appear artificially normal. That is why the raw number should be interpreted alongside albumin concentration and the patient’s overall state.
In practice, the most useful approach is to interpret results in context:
- A normal gap with low bicarbonate may suggest a non-gap metabolic problem. Low bicarbonate with a high gap points toward a gap metabolic acidosis pattern. Reduced albumin can decrease the apparent gap and obscure a true abnormality.
Corrected Anion Gap and Albumin Correction
Because albumin plays a major role in the anion gap, hypoalbuminemia can mask a true elevation. Under those circumstances, a corrected anion gap is more clinically meaningful than the unadjusted value. The goal is to correct for albumin so the result more accurately reflects the patient’s actual acid-base state.
Multiple albumin correction approaches, but the key idea is straightforward: lower albumin lowers the observed anion gap. If albumin is reduced, the clinician should consider a correction before concluding that the gap is normal.
One common correction method adds a set amount to the measured gap for each decrement in albumin below normal. The exact adjustment may vary by formula, so a calculator https://anion-gap-calculation.com/acid-base-disorders/toxins.html that includes albumin can be especially helpful. The important clinical principle is that hypoalbuminemia can hide a high anion gap.
This matters because: a patient with low albumin and elevated lactate may have a corrected value that changes interpretation significantly. Without adjustment, the raw anion gap can miss the severity of the metabolic derangement.
Review this clinical reasoning:
- The observed gap seems normal. Albumin is low. With albumin adjustment, the gap becomes elevated.
That shift can expose hidden acidosis and support further evaluation. In other words, the corrected anion gap is not just a mathematical exercise. It is a method to avoid missing clinically important acid-base abnormalities.
When using an anion gap calculator, always check whether it includes albumin input or provides a separate albumin correction field. If not, you may need to modify the number manually when albumin is abnormal.
Typical Causes of an Abnormal Anion Gap
A widened gap is usually a sign that something is changing the body’s acid balance or electrolyte pattern. The most common causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and toxins.
Lactic acidosis develops when lactate builds up because tissues are not using oxygen effectively or because metabolism is stressed. This often appears in severe illness, shock, hypoperfusion, or other states of tissue hypoxia. The extra lactate acts as an unmeasured anion and raises the gap.
Ketoacidosis appears when ketone bodies build up, commonly in diabetes but also in starvation or alcohol-related states. These ketones cause metabolic acidosis and widen the gap.
Renal failure can also cause an elevated gap because impaired kidneys do not eliminate acids effectively. As acids accumulate, the plasma shows more unmeasured anions and less bicarbonate.
Toxins are another important category. Certain ingestions bring in acids or acid precursors that produce a high-gap pattern. In these cases, the anion gap may provide an early signal that directs urgent evaluation.
Common reasons for a normal anion gap with acidosis include gastrointestinal bicarbonate loss or renal tubular causes. In those cases, chloride often rises to replace lost bicarbonate, which is why the gap can remain normal despite serious illness.
Helpful pattern recognition can be summarized this way:
- High anion gap: suspect extra acids or retained acid. Normal anion gap: suspect bicarbonate loss with compensatory chloride rise. Always check sodium, chloride, bicarbonate, and the full clinical picture.
Clinical Overview and Acid-Base Imbalances
Anion gap is especially helpful when considered within the broader context of acid-base disturbances. It is just one part of the picture. A patient may have a metabolic alkalosis, ventilatory acidosis, or mixed condition in addition to an abnormal gap, and the overall pattern is more important than the value itself.

In alkalotic states, bicarbonate is increased rather than reduced, so the anion gap is not the key sign. Still, the gap may help identify a mixed condition if a patient has both alkalosis and a hidden high-gap process.
In carbon dioxide retention, carbon dioxide retention is the main problem, not an isolated bicarbonate change from acid accumulation. However, persistent respiratory problems can lead to secondary changes in bicarbonate that complicate interpretation. The anion gap can help identify or dismiss an accompanying metabolic disorder.
This is why a good interpretation of acid-base status uses more than one number. A clinician may review pH, CO2, bicarbonate, sodium, chloride, and albumin together. The anion gap then becomes a useful clinical tool for identifying whether the disturbance is metabolic, respiratory, or mixed.
Another helpful concept is the delta gap. This compares the rise in anion gap with the fall in bicarbonate and can suggest whether more than one metabolic process is happening at once. It is especially useful when the clinical picture does not match the expected pattern. A delta gap can reveal a hidden metabolic alkalosis or an additional non-gap acidosis alongside a high-gap disorder.
Practically speaking, the anion gap supports bedside reasoning:
- Is there acid-base acidosis? Is the gap increased or within range? Is albumin low enough to require compensation? Do the results fit the symptoms and other laboratory values?
FAQ
What is the anion gap calculator with serum sodium for?
This anion gap calculator with serum sodium is designed to rapidly calculate anion gap from routine blood chemistry values. It assists in assess acid-base balance, detect possible metabolic acidosis, and identify patterns such as a high anion gap or normal anion gap. It is particularly useful when reviewing an electrolyte panel that includes sodium, chloride, and bicarbonate.
How is anion gap calculated from sodium, chloride, and bicarbonate?
Follow the standard anion gap formula: sodium − (chloride + bicarbonate). Enter the measured sodium, chloride, and bicarbonate values, then subtract the sum of chloride and bicarbonate from sodium. This yields the calculated gap, which can then be compared with the normal reference range.
What is considered a normal anion gap?
A normal anion gap is based on the laboratory’s method and reference interval, so the best answer is the range printed with the test results. In many settings, the normal reference range is relatively narrow. Always remember to interpret the result using the lab’s reported range and the patient’s overall clinical picture, especially if albumin is abnormal.
Why correct the anion gap for albumin?
You correct the anion gap for albumin because low albumin can make the measured gap look falsely normal. With hypoalbuminemia, a true elevation may be hidden. A corrected anion gap gives a more accurate estimate of the acid-base state by adjusting for the loss of this major unmeasured anion. For this reason many clinicians choose to correct for albumin when interpreting results.
What does a high anion gap usually mean?
A high anion gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. It often points to metabolic acidosis, but the result should always be interpreted with other laboratory values, symptoms, and the full acid-base pattern.