What Is the Anion Gap?
The anion gap is a computed value that is used to assess acid-base status by contrasting the main measured electrolytes in a blood sample. It is typically calculated from a serum chemistry panel or other serum electrolytes results, using the relationship between sodium, chloride, and bicarbonate. Clinically, it helps identify whether there are unmeasured anions contributing to an anion deficit and an underlying acid-base disorder.
In simple terms, the anion gap is a diagnostic tool that estimates the difference between positively charged and negatively charged particles in the blood. That difference reflects electrolyte balance and can point to a metabolic disturbance that is not obvious from the individual values alone. Because it is based on routine blood chemistry, it is often used as a screening test during patient assessment.
Most modern labs provide the ingredients needed for the calculation as a standard laboratory result. Even though the concept sounds abstract, the practical use is straightforward: if the gap is elevated, clinicians think about causes of metabolic acidosis, especially high anion gap metabolic acidosis.
Anion Gap Calculation Formula Without K
The standardly used calculation method without potassium is given by:
Anion gap = sodium - (chloride + bicarbonate)
This formula uses sodium value, serum chloride, and serum bicarbonate results from the lab. When you use an Anion Gap Calculator, this is typically the default approach because it is more straightforward and aligns with common clinical use.
All values are typically reported in mEq/L. The formula deducts the combined amount of chloride and bicarbonate from sodium. Since sodium is the principal measured cation in the panel, and chloride plus bicarbonate are the principal measured anions, the result reflects the space left by anionic charge from unmeasured substances.
While some older formulas also included potassium, many clinicians omit it because the contribution is small and rarely changes the practical medical interpretation. A simplified formula makes the calculation easier without sacrificing much utility in routine use.
When checking the result manually, make sure the units align and that the numbers come from the same test values set. An error in units or transcription can alter the result significantly.
Stepwise Math Demo
Below is a simple example calculation based on typical laboratory values:
- Sodium = 140 mEq/L Cl = 102 mEq/L HCO3 = 24 mEq/L
Using the calculation:
Anion gap = 140 - (102 + 24)
To begin add chloride and bicarbonate:
102 + 24 = 126
Then take away from sodium:
140 - 126 = 14
This value is 14 mEq/L. Based on the lab expected range, this may be considered normal or mildly elevated. For that reason the result must always be interpreted in context rather than as a stand-alone number.
Using an anion gap calculator can help prevent arithmetic mistakes, but the manual method is easy to check. The key is to remember the exact method and to use current lab values rather than outdated results. When values change rapidly, the gap can shift along with the patient’s blood acid-base status.
Normal Values and Analysis
A expected anion gap depends on the laboratory reference interval, the analysis method, and whether potassium is included. In many cases, a common non-potassium result is roughly in the low teens, but the exact reference range differs from one lab to another. Always compare the number with the lab’s stated range instead of relying on a universal cutoff.
A raised anion gap suggests extra unmeasured acids in the blood. This pattern is commonly associated with metabolic acidosis, especially high anion gap metabolic acidosis. The finding can help focus the differential diagnosis, but it does not identify the cause by itself.
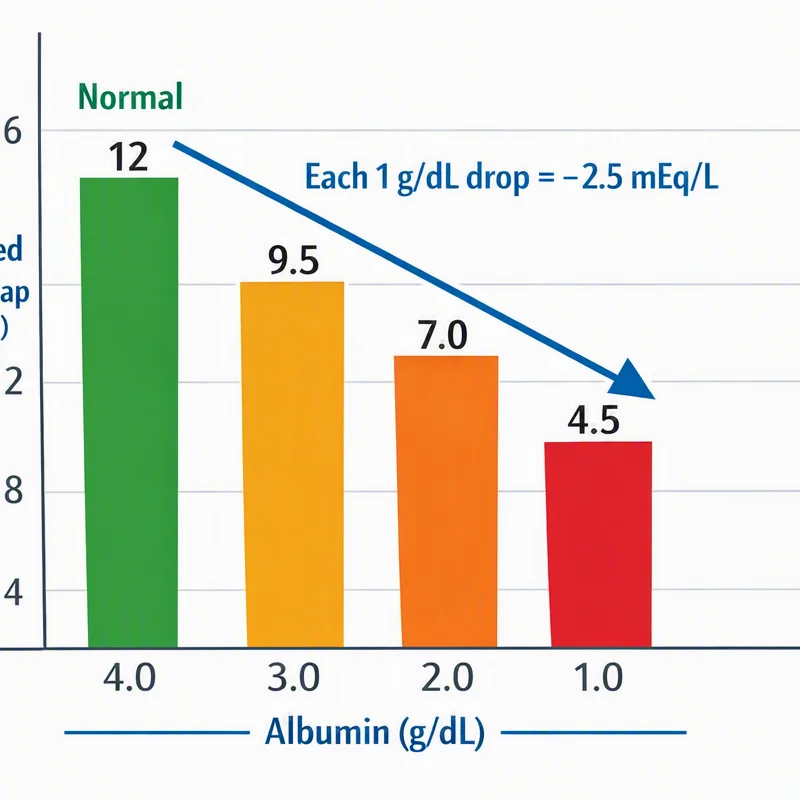
One important factor is albumin. Because albumin is a major unmeasured anion, low albumin can make the anion gap appear lower than expected. In those cases, clinicians may use an albumin-corrected anion gap to get a more accurate corrected value. This is especially useful when evaluating a suspected acid-base disorder in patients with hypoalbuminemia.
Interpretation should also distinguish high-gap from non-anion gap metabolic acidosis. A normal gap does not rule out acidosis; it may indicate bicarbonate loss with a compensatory rise in chloride, as seen in normal-gap patterns. That is why the number should always be viewed alongside the full chemistry panel and the broader clinical picture.
Why Potassium Is Often Omitted
Potassium is often left out because its concentration is significantly lower than sodium, and the difference typically has little impact on everyday clinical practice. The simplified formula enhances consistency and accelerates use in busy settings. Many forms of laboratory reporting also exclude potassium for this reason.
From a practical standpoint, leaving potassium out makes the calculation easier to remember and lowers the chance of error. The change in result is often slight enough that it does not affect the general conclusion, especially when the goal is initial screening rather than advanced analysis.
That said, the omitted-potassium method is not a different concept. It is the same physiologic idea, just a streamlined approach built into many calculators and lab systems. If an older source includes potassium, the resulting number will be marginally higher, but the overall assessment of acid-base status often is similar.
In other words, the anion gap calculator commonly used in practice is based on the abbreviated formula because it is effective, reproducible, and appropriate for most patient assessment scenarios.
Origins of a Increased Anion Gap
A high result indicates extra acid or hidden anions in the bloodstream. Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Each of these can elevate the gap for a different reason, but all lead to an rise in hidden acids.
Lactic acidosis develops when lactate builds up, often in settings of poor perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis arises when ketones build up, such as in diabetes or prolonged fasting. Renal failure can decrease acid excretion, causing acids to collect. Toxic ingestions may introduce substances that are metabolized into acids or that interfere with normal metabolism.
These causes are especially important when the anion gap is elevated with signs of metabolic acidosis. A clinician may use the gap as a clue, then combine it with history, physical findings, and additional testing to find the underlying problem. The gap itself is a clue, not a final diagnosis.
Because different disorders can produce the same pattern, the value should be considered part of a larger diagnostic framework. A patient with high-gap acidosis needs a focused evaluation, and the anion gap calculator can help flag the issue early.
Limitations of the Anion Gap Calculator
An anion gap calculator is useful, but it has key drawbacks. The main is albumin adjustment. Since albumin is a major contributor to the normal gap, low albumin can hide a clinically meaningful elevation. If not adjusted, the result may look falsely reassuring.
Also, the value depends on the laboratory’s reference range. Different techniques, machines, and result-reporting procedures can produce different values, so a finding that appears unusual in one setting may be acceptable in another. This is why interpretation should always be tied to the specific laboratory’s reference interval.
Thirdly, testing error can skew the result. Contaminated samples, delayed processing, or transcription mistakes can alter sodium, chloride, or bicarbonate values. Since the gap is calculated from these components, even one inaccurate laboratory result can cause a incorrect conclusion.
Ultimately, the result is only a single part of the evaluation. It does not replace a complete medical review, arterial or venous blood gas when appropriate, or evaluation for other sources of acid-base disturbance. When used correctly, it is a reliable screening measure; by itself, it can be incomplete.
Common Questions
How do you calculate anion gap without potassium?
Apply the formula sodium - (chloride + bicarbonate). https://anion-gap-tool964.fotosdefrases.com/anion-gap-calculator-for-metabolic-acidosis-assessment This is the typical streamlined method and is how most anion gap calculator tools use. Type in the lab values in mEq/L and subtract the sum of chloride and bicarbonate from sodium.
What is the formula for an anion gap calculator without potassium?
The formula is anion gap = sodium - (chloride + bicarbonate). It uses the main serum electrolytes from the lab panel and leaves out potassium for ease. This remains the most widely used calculation formula in daily practice.
What is a normal anion gap without potassium included?
The normal values vary by the lab’s normal range and testing method. Many labs consider a low teen result normal when potassium is excluded, but you should always compare the number to the reported lab range on that specific test result.
Why is potassium often left out of the anion gap calculation?
K is usually excluded because it contributes minimally to the overall result. Leaving it out creates a streamlined formula that fits common day-to-day practice and laboratory reporting standards without meaningfully changing everyday clinical assessment.
What does a high anion gap mean clinically?
A high result suggests extra unmeasured acids and is often associated with acidotic states, especially high anion gap metabolic acidosis. Common causes include lactate buildup, ketoacidosis, renal failure, and toxin exposure. The value supports evaluation, but the cause requires further assessment.